
Volume 23, Issue 2 (6-2026)
J Res Dev Nurs Midw 2026, 23(2): 57-64 |
Back to browse issues page


Download citation:
BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:


BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:
Taghavi Deghdeghdn A, Sheikhi M R, Vahidi M, Ranjbaran M. Effect of the Family-Centered Empowerment Model on self-care requisites in patients with schizophrenia: A randomized controlled trial. J Res Dev Nurs Midw 2026; 23 (2) :57-64
URL: http://nmj.goums.ac.ir/article-1-2335-en.html
URL: http://nmj.goums.ac.ir/article-1-2335-en.html


1- Department of Psychiatric Nursing, School of Nursing and Midwifery, Qazvin University of Medical Qazvin, Qazvin, Iran
2- Department of Psychiatric Nursing, School of Nursing and Midwifery, Qazvin University of Medical Qazvin, Qazvin, Iran ,mmsheikhi1@yahoo.com
3- Department of Psychiatric Nursing, School of Nursing and Midwifery, Tabriz University of Medical Sciences, Tabriz, Iran
4- Non-communicable Diseases Research Center, Research Institute for Prevention of Non-communicable Diseases, Qazvin University of Medical Sciences, Qazvin, Iran
2- Department of Psychiatric Nursing, School of Nursing and Midwifery, Qazvin University of Medical Qazvin, Qazvin, Iran ,
3- Department of Psychiatric Nursing, School of Nursing and Midwifery, Tabriz University of Medical Sciences, Tabriz, Iran
4- Non-communicable Diseases Research Center, Research Institute for Prevention of Non-communicable Diseases, Qazvin University of Medical Sciences, Qazvin, Iran
Full-Text [PDF 553 kb]
(174 Downloads)
| Abstract (HTML) (1173 Views)
Discussion
The present randomized controlled trial provides evidence that the Family-Centered Empowerment Model significantly improves the fulfillment of self-care requisites in patients with schizophrenia, as reflected by a significant reduction in SCRS-H scores. The intervention group demonstrated a mean reduction of approximately 4.5 points on the Self-Care Requisites Scale in Schizophrenia (SCRS-H), with a moderate-to-large effect size. This improvement remained significant after controlling for baseline differences and education levels, supporting the robustness of the findings. These findings suggest that training primary caregivers through a structured, family-centered approach can enhance patients' fulfillment of self-care requisites, including those related to activities of daily living, treatment adherence, and health-status monitoring. Improved fulfillment of these self-care requisites may contribute to better community functioning and a reduced risk of relapse.
The observed improvement is consistent with previous family-based interventions in schizophrenia. Rodolico et al. (2022) and Chien et al. (2024), in their systematic reviews, reported that family psychoeducation reduces relapse rates and improves clinical outcomes, though they did not specifically measure self-care (20,9). More directly, Zhou et al. (2020) found that empowerment-based approaches for family caregivers improved patient functioning, while Iswanti et al. (2024) highlighted family empowerment strategies as key to relapse prevention (29,25). Our findings extend this evidence by demonstrating that the Family-Centered Empowerment Model-with its emphasis on perceived threat, problem-solving, and educational participation-can specifically target self-care deficits, an outcome that has received less attention in previous trials.
Several mechanisms may explain this effect. First, the model enhances caregivers' knowledge of schizophrenia and its management, enabling them to provide more informed and consistent support (24). Second, by training caregivers in problem-solving and communication skills, the intervention likely improves the quality of interactions between patients and families, fostering a home environment conducive to self-care practice. Third, Bandura's self-efficacy theory suggests that when family members model and reinforce positive health behaviors, patients develop greater confidence in their own ability to perform self-care tasks (30). This indirect pathway-through the caregiver rather than the patient-may be particularly effective in schizophrenia, where cognitive and motivational deficits often limit the impact of patient-only education.
From a clinical perspective, the Family-Centered Empowerment Model offers several advantages (31). It is relatively low-cost, leverages existing family resources, and can be integrated into routine psychiatric care without requiring extensive additional infrastructure. The group-based format (6-7 caregivers per session) also facilitates peer learning and shared problem-solving, which may enhance caregiver motivation and reduce isolation. These features make the model a practical adjunct to pharmacotherapy, particularly in resource-limited settings where access to specialized mental health services is constrained.
The positive effect of the intervention persisted despite baseline differences in education levels between groups, suggesting that the model may be adaptable across varying socioeconomic backgrounds. Nonetheless, this finding should not be overgeneralized, as the study sample was drawn from a single hospital in Tabriz and may not represent the broader schizophrenia population in Iran. Factors such as symptom severity, medication regimen, illness duration, cognitive functioning, and extra-familial social support-which were not fully controlled-may have influenced outcomes and should be examined in future research.
The legal and ethical considerations associated with family-oriented interventions, including negligence and informed consent, merit attention in future implementation studies (32-34). However, these issues are general to family-based care and do not directly affect the interpretation of our primary findings.
Several limitations should be considered when interpreting these findings. First, the study was conducted in a single psychiatric center with a relatively small sample, which may limit the external validity of the results. Second, blinding of participants and caregivers was not feasible because of the nature of the intervention, although outcome assessment was performed by a blinded assessor to minimize detection bias. Third, residual confounding cannot be excluded, as clinical characteristics such as symptom severity, medication regimen, duration of illness, cognitive functioning, and extra-familial social support were not fully controlled. In addition, self-care was assessed using a self-report instrument, making the findings susceptible to response and social desirability biases, as well as the limited insight commonly observed in schizophrenia. Finally, because the minimal clinically important difference (MCID) for the SCRS-H has not yet been established, the clinical relevance of the observed score changes should be interpreted cautiously. Future studies should evaluate this intervention in larger, multicenter populations with longer follow-up periods, objective outcome measures, and clinically meaningful endpoints to determine the durability and clinical significance of its effects.
Conclusion
This randomized controlled trial demonstrated that the Family-Centered Empowerment Model improved self-care requisites in patients with schizophrenia compared with routine care, as reflected by lower SCRS-H scores. By actively engaging family caregivers in the rehabilitation process, this structured and relatively low-cost intervention has the potential to complement routine psychiatric care and strengthen patients' self-care capacity. Although the findings are encouraging, confirmation in larger multicenter randomized trials with extended follow-up is required before broad implementation can be recommended. Future research should also identify the patient and family characteristics associated with the greatest benefit, clarify the mechanisms underlying the intervention, and establish the minimal clinically important difference for the SCRS-H.
Acknowledgement
The authors would like to thank the patients and their caregivers for their sincere participation. We also appreciate the cooperation of the staff at Razi Hospital, Tabriz, and the Research Vice-Chancellor of Qazvin University of Medical Sciences.
Funding Sources
This research received no specific grant from any funding agency in the public, commercial, or not for profit sectors.
Ethical Statement
The study was approved by the Research Ethics Committee of Qazvin University of Medical Sciences (Approval No. IR.QUMS.REC.1404.001) and was conducted in accordance with the Declaration of Helsinki and relevant national ethical guidelines. Before enrollment, all participants (Patients and their primary caregivers) received clear information about the study objectives, procedures, and their rights. Written informed consent was obtained from all participants prior to data collection. Participation was voluntary, and participants were informed that they could withdraw from the study at any time without affecting their treatment or healthcare services. The confidentiality of all personal and medical information was strictly maintained by anonymizing and securely storing the study data. To ensure equitable access to the educational intervention, caregivers in the control group were provided with a summary training session and educational pamphlets after completion of the study.
Conflicts of Interest
The authors declare no conflict of interest.
Author Contributions
A.T.D: Conceptualization, Investigation, Data collection, Writing - Original draft. M.Sh.: Supervision, Methodology, Project administration, Writing - Review and Editing. M.V: Investigation, Validation, Writing - Review and Editing. M.R: Formal analysis, Software, Data curation. All authors read and approved the final manuscript.
Data Availability Statement
The data supporting the findings of this study are available from the corresponding author upon reasonable request, subject to ethical restrictions.
Use of Artificial Intelligence
We used AI to improve the language. After using this service, the authors reviewed and edited the content as needed and take full responsibility for the content of the published article.
Full-Text: (22 Views)
Introduction
Schizophrenia is a severe, chronic psychiatric disorder affecting approximately 24 million people globally, with a lifetime prevalence of about 1% in Iran and a substantial burden in disability-adjusted life years (DALYs) (1). This burden underscores the urgent need for effective, low-cost interventions, such as family-based empowerment programs. Like other chronic conditions, schizophrenia requires continuous long-term care, with nurses serving as frontline providers who maintain prolonged contact with patients and their families (2).
Self-care has emerged as a major concern in chronic disease management (3). Orem defines self-care as a dynamic process involving activities in which individuals engage to maintain their health (4). In schizophrenia, self-care encompasses activities of daily living (Personal hygiene, nutrition, and sleep), medication management, symptom monitoring, coping with stress, and social connection. Deficits in these areas lead to poor outcomes, frequent relapses, and reduced quality of life (5).
Patients with schizophrenia require multiple self-care interventions: medication management for symptom control; psychological and social support to prevent isolation; education about the illness and its management; physical healthcare (Nutrition, exercise, and sleep); and stress-management techniques (6,7). Healthcare providers and families can promote self-care through community-oriented approaches that delegate care responsibilities to patients and their families (8).
Family education is particularly influential in chronic mental illness. Effective training reduces psychological problems, improves health and patient satisfaction, enhances quality of life, ensures continuity of care, reduces complications, shortens hospital stays, increases independence, and enables home-based recovery (9). Research indicates that inadequate education remains a major concern among patients with schizophrenia and their families (10). Empowering families is critical because they provide primary emotional support, help patients understand their emotions and requisites, and must learn about schizophrenia symptoms, treatments, and management strategies to reduce stress (11).
The Family-Centered Empowerment Model enhances family roles in motivation, psychological support, knowledge, attitudes, and perceived threat (12). Empowerment fosters trust, positive adaptation, control, and goal achievement (13). By increasing awareness and self-efficacy, empowerment promotes behavioral self-control, preventive behaviors, health promotion, and improved quality of life (14). Family empowerment creates the capacity for change through nurse-family partnerships and shared responsibility (15). This model has shown positive effects in chronic conditions, including diabetes, heart failure, elderly care, and hemodialysis (16-19). However, no study has specifically examined family-centered care for improving self-care among patients with schizophrenia.
Schizophrenia affects not only the individual but also the family and society, necessitating effective strategies to improve quality of life and reduce the burden of family care (20). The Family-Centered Empowerment Model can improve self-care requisites by increasing family awareness, improving communication, reducing tensions, and enabling patients to cope independently with daily challenges (21). Enhanced self-care reduces symptoms, prevents rehospitalization, improves mental and physical health, and reduces healthcare costs.
Despite the importance of education, many families lack awareness of the specific self-care requisites of patients with schizophrenia and the effective methods for addressing them (22). Sufficient educational resources and family programs focused on self-care skills are lacking (23). Although family-based interventions in schizophrenia have focused on relapse prevention, symptom management, or caregiver psychoeducation, few studies have targeted self-care as the primary outcome, and none have applied the Family-Centered Empowerment Model-which emphasizes perceived threat, problem-solving, and educational participation-to improve daily self-care (22,24,25). This gap justifies the present trial.
Unlike previous studies that focused on relapse prevention or general family psychoeducation, this trial specifically targeted self-care using the structured Family-Centered Empowerment Model among Iranian patients with schizophrenia who had been discharged from a large psychiatric hospital. Therefore, this study aimed to determine the effect of the Family-Centered Empowerment Model on self-care requisites in patients with schizophrenia.
Methods
Design and setting
This randomized controlled trial investigated the effect of the Family-Centered Empowerment Model on self-care requisites in patients with schizophrenia discharged from Razi Hospital in Tabriz, Iran. Razi Hospital is one of the largest teaching hospitals in East Azerbaijan Province and the only center admitting psychiatric patients in the region. It has 18 wards with 650 active beds (591 psychiatric, 68 non-psychiatric) and paraclinical departments. Patients with schizophrenia who were about to be discharged were identified, and their primary caregivers were invited to participate. The primary caregivers then received the training necessary to empower families to improve patients' self-care requisites.
Patients were eligible if they had a diagnosis of schizophrenia according to the Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition (DSM-5), resided in Tabriz, had been discharged from the psychiatric ward of Razi Hospital, provided informed consent (Or consent was obtained from their legal guardian when applicable), adhered to their prescribed medication regimen, and had no comorbid psychiatric disorders (e.g., personality disorders) or severe chronic physical illnesses (e.g., advanced renal or cardiovascular disease) that could interfere with participation. Patients were excluded if they experienced a psychiatric emergency during the study or withdrew their consent.
Primary caregivers were eligible if they were identified by the patient as the family member providing the greatest amount of care, were aged 18 years or older, were able to read and write, had no self-reported mental or psychological illness, and were willing to participate in the study. Caregivers were excluded if they missed more than two consecutive training sessions, were unable to continue participation because of personal circumstances, or declined to continue with the family-centered intervention.
Participants and sampling
The sample size was calculated based on a previous study (26) that reported post-intervention means of 82.08 ± 10.88 (Intervention) and 93.42 ± 16.05 (Control). Although our baseline self-care scores were somewhat worse than those in the reference study, we used a conservative approach: we adopted the larger standard deviation (16.05) from the control group and set the power at 90% to account for potential baseline differences and ensure adequate power to detect a clinically meaningful difference. With a type I error of 0.05 and a mean difference of 10 points, the required sample size was 33 per group; after adding 10% for possible attrition, the final sample was set at 36 per group. This conservative calculation was complemented by the post-hoc sensitivity analysis.
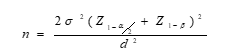
The 72 patients were randomly allocated to the intervention (n = 36) or control (n = 36) group. All 36 participants in each group completed the 8-week intervention and follow-up period; no participants were lost to follow-up, and no one was excluded during the study. Thus, 36 participants in each group (72 in total) were included in the final analysis. A detailed CONSORT flow diagram is provided in Supplementary Figure 1. Although the sample-size calculation anticipated a 10% dropout rate, no attrition occurred during the 8-week study period. All 36 patients in each group completed the post-test assessment.
Data collection
After obtaining official permission from the Research Vice-Chancellor of Qazvin University of Medical Sciences, which supervised the research team, and securing local approval from Tabriz University of Medical Sciences to access Razi Hospital, the research team visited the hospital. Eligible individuals were selected and invited to participate. Written informed consent was obtained from all participants. The patients completed the questionnaires themselves in a quiet room, with the researcher present only to read the items aloud to patients with literacy difficulties or concentration problems. The researcher did not interpret, rephrase, or influence the patients' responses. Eligible patients and their caregivers were selected using purposive sampling from among those discharged from Razi Hospital during the study period. After selection, participants were randomly allocated to the intervention and control groups using block randomization (Block size of 4) to ensure unbiased assignment.
Participants were assigned to the intervention or control group using block randomization (Block size of 4). For 72 participants, 18 blocks were created, each containing 2 intervention and 2 control assignments. Block sequences (e.g., ABAB, AABB, ABBA, and BAAB) were determined using a random-numbers table. To conceal allocation, 72 envelopes were prepared; each random sequence (1 to 18) was recorded on a card and placed in an envelope. The envelopes were sealed and placed sequentially in a box. One envelope was opened at a time, and allocation was based on the block it contained.
Patients who were about to be discharged were identified. The study objectives and procedures were explained to each patient and primary caregiver, and written informed consent was obtained. A pretest was then administered to the patient. Groups of 6-7 participants were formed, and training sessions were conducted as described below. After briefing the patients and their active family members (The primary caregivers identified by the patients), the researcher and an assistant administered the pretests in the psychiatric wards. The following questionnaires were completed: a demographic form (Age, gender, marital status, employment, disease history, etc.) and the Self-Care Requisites Scale in Schizophrenia (SCRS-H) developed by Roldán-Merino (2017) (27). The questionnaire yields a total score ranging from 33 to 165. A lower score indicates a smaller self-care deficit. The questionnaires were completed by the patients themselves.
Both groups received routine psychiatric ward care, including vital-sign monitoring, medication prescription and education, a physician-ordered diet, activity education, and discharge planning. The research team provided no additional intervention to the control group. In the intervention group, the researcher trained the primary caregivers in the ward’s education room after the patients' conditions had stabilized. By agreement with the participants and in consideration of existing constraints, training sessions were held once a week for 8 weeks (9-11 AM). Each session lasted 30-60 minutes. The educational content was designed and implemented based on a needs assessment and the characteristics of the study population. Training was delivered in person using a family-centered approach.
Due to the nature of the educational intervention, it was not possible to blind patients or their primary caregivers to group allocation. However, the outcome assessor who administered the self-care questionnaire was blinded to group assignment to minimize detection bias. The statistician was not blinded to group allocation. All data were collected and entered into the statistical software by a research assistant who was unaware of the study hypotheses.
Intervention
The educational program was based on the Family-Centered Empowerment Model described by Nikrouz et al. (2020) (28). The model consisted of four main steps implemented over 8 weekly sessions for primary caregivers in the intervention group. Sessions were conducted in groups of 6-7 caregivers, who were assigned to groups based on their availability and discharge schedules (Group composition was not randomized). Each session lasted 30 to 60 minutes, depending on the content and group interaction, and was delivered in person in the hospital education room. All sessions were group-based rather than individual to facilitate peer learning and shared problem-solving. A summary of the procedure follows:
Step 1: Perceived threat (Session 1) - Caregivers learned about schizophrenia, its course, symptoms (Positive, negative, cognitive), complications, risk factors, and prognosis. The main goal was to increase awareness and understanding of the disease as a manageable challenge.
Step 2: Problem-solving (Sessions 2-4) - Caregivers were taught necessary self-care requisites for the patient. Content included:
Session 2: Healthy nutrition, physical activity, medication adherence, personal hygiene, interpersonal communication.
Session 3: Identifying and analyzing common patient problems (e.g., non-adherence, communication difficulties) and the family’s role in solving them.
Session 4: Explaining treatment and self-care goals, presenting various solutions for identified problems, and selecting the best solution through group participation.
Step 3: Educational participation (Sessions 5-7) - Sessions were conducted as group discussions and Q&A activities. Caregivers raised practical challenges they encountered when implementing the selected solutions at home. Through discussion and guidance from the researcher, they developed new and more effective solutions. These sessions helped consolidate learning and improve caregivers’ practical skills.
Step 4: Evaluation (Session 8) - The final session assessed caregivers’ knowledge and ability to transfer the information and skills they had learned to patients and other family members. Evaluation was conducted through Q&A activities and group discussion.
It is important to emphasize that patients did not attend the group sessions. Instead, the intervention was designed as a train-the-trainer model: caregivers received knowledge and practical skills during the sessions and were then expected to transfer and practice these skills with the patients at home between sessions. The final evaluation session (Step 4) specifically assessed each caregiver's ability to transfer the learned content to the patient and other family members. Thus, improvement in patients' self-care was achieved indirectly through empowered caregivers, consistent with the core philosophy of the Family-Centered Empowerment Model.
Instruments
Data were collected using a demographic form and the Self-Care Requisites Scale in Schizophrenia (SCRS-H) developed by Roldán-Merino (27). The questionnaires were completed in person by patients as self-reports, with assistance from the researcher when required.
The demographic form included age, gender, education level, occupation, marital status, income level, and disease duration.
The SCRS-H was developed by Roldán-Merino (2017) (27) and culturally adapted for the Iranian population by Kashani Lotfabadi (2022), with a Cronbach’s alpha > 0.70. This scale assesses the self-care requisites of hospitalized patients with schizophrenia (26). It consists of 35 items, each rated on a 5-point scale (1 = no self-efficacy deficit, 5 = complete self-efficacy deficit). Total scores range from 35 to 175; lower scores indicate fewer self-care deficits (i.e., better fulfillment of self-care requisites).
The scale was developed in two stages. First, items based on Orem’s nursing theory were reviewed and approved by a team of 9 mental health specialists and a psychiatrist. Second, psychometric properties were confirmed through confirmatory factor analysis in 264 hospitalized schizophrenia patients (27). Roldán-Merino et al. (2017) confirmed validity and internal consistency (Cronbach’s alpha = 0.94 for the total scale) (27).
Kashani Lotfabadi (2022) adapted the scale for Iran. The translation process was as follows: two Persian-fluent translators translated the scale into Persian; two other translators back-translated the approved Persian version; and a third translator fluent in both languages compared and confirmed the original English and back-translated versions. The Persian translation was then reviewed by a team of 10 clinical psychologists, psychiatrists, and psychiatric nurses. The content-validity indices were CVI = 0.79 and CVR = 0.83 (26). Internal consistency for the total scale was Cronbach’s alpha = 0.88. In the present study, face and content validity were assessed by 10 faculty members of Qazvin University of Medical Sciences, and internal consistency (Cronbach's alpha) was 0.91, indicating excellent reliability. However, construct validity (e.g., confirmatory factor analysis) and test-retest reliability were not re-established for the current sample because the primary aim was to evaluate the intervention effect rather than validate the instrument in this specific population.
Data analysis
Data were analyzed using SPSS version 25. Quantitative variables were described using means and standard deviations, and categorical variables were described using frequencies and percentages. Independent t-tests were used to compare demographic distributions between groups. An independent t-test was also used to compare pre-test self-care scores between the intervention and control groups. To test the hypothesis, analysis of covariance (ANCOVA) was performed with the post-test self-care score as the dependent variable, group as the fixed factor, and pre-test score, patient education level, and caregiver education level as covariates. The educational intervention was provided only to the primary caregivers; patients did not attend the group sessions. Given the borderline interaction between group and pre-test score (P = 0.058) for the homogeneity-of-regression-slopes assumption, a sensitivity analysis was also conducted using a linear mixed-effects model with random intercepts to confirm the robustness of the findings.
Results
A total of 72 patients with schizophrenia and their primary caregivers were randomly assigned to the intervention (n = 36) or control (n = 36) group. The baseline characteristics of patients and caregivers are presented in Tables 1 and 2. The two groups were comparable across most baseline demographic and clinical characteristics. However, significant between-group differences were observed in the education levels of both patients (P = 0.048) and caregivers (P = 0.013). These variables were therefore included as covariates in the adjusted analyses.
The normality of self-care requisites scores in the intervention and control groups was examined separately for the pre-test and post-test and confirmed using histograms and Q-Q plots, as well as the Kolmogorov-Smirnov test (P > 0.05 for all).
As shown in Tables 1 and 2, the intervention and control groups were well matched in terms of baseline demographic and clinical characteristics, supporting the effectiveness of randomisation. Minor imbalances in patient and caregiver education levels were statistically adjusted for as covariates in the primary analysis.
As presented in Table 3, the intervention group showed a significant reduction in self-care requisites scores after the intervention (Post-test: 90.72 ± 12.19), whereas the control group showed little change (Post-test: 100.22 ± 15.03). The between-group difference at the post-test was statistically significant (P = 0.004). Paired t-tests confirmed a significant within-group improvement in the intervention group (Mean change: -4.44 ± 3.12, t = 7.12, P < 0.001), whereas the control group experienced no significant change (Mean change: - 0.20 ± 2.85, t = 0.42, P = 0.678). These within-group findings justified the use of ANCOVA to adjust for baseline differences and covariates.
Levene’s test was used to examine the homogeneity of error variances for the self-care requisites variable. The result (F = 1.22, P = 0.272) showed that the assumption of equal error variances between the groups was met (P > 0.05).
Analysis of covariance assumes a linear relationship between the covariate (Pre-test self-care score) and the dependent variable (Post-test self-care score). The homogeneity-of-regression-slopes assumption concerns the relationship between the covariate and the dependent variable. This assumption was tested by examining whether the interaction between the independent variable (Group) and the covariate (Pre-test score) was statistically significant. The interaction was not significant (F = 2.24, P = 0.058), confirming that the homogeneity-of-regression-slopes assumption was met.
As shown in Table 4, after controlling for pre-test scores, the effect of the intervention on reducing the total self-care requisites score was statistically significant (P < 0.001). The effect size, measured using partial eta squared (η²), was 0.78, indicating that 78% of the variance in post-intervention self-care requisites scores was explained by the Family-Centered Empowerment Model intervention. Because the distributions of patient and caregiver education levels differed significantly between the two groups, we conducted an additional analysis adjusting for these two variables. After controlling for pre-test scores and education levels, the intervention effect on reducing the total self-care requisites score remained statistically significant (P < 0.001). The partial eta squared (η²) effect size was 0.75, indicating that 75% of the variance in the total post-intervention self-care requisites score was explained by the Family-Centered Empowerment Model intervention. The corresponding Cohen's d was 0.69 (95% CI: 0.21 to 1.17).
Because the homogeneity-of-regression-slopes assumption was borderline (Group × pre-test interaction: P = 0.058), we reanalyzed the data using a linear mixed-effects model. The intervention effect remained statistically significant in this sensitivity analysis (β = - 9.21, SE = 0.87, P < 0.001), confirming that the results were robust to the choice of statistical method. Despite the baseline imbalance in education, which could increase error variance, a post-hoc power analysis was performed using the observed effect size (Cohen’s d = 0.69), with α = 0.05 and a sample size of 36 per group. The achieved power was 0.94, indicating that the study had sufficient power (Above the conventional 0.80 threshold) to detect the intervention effect, even after accounting for baseline differences. This result confirms that the observed significant findings were unlikely to be attributable to insufficient power.
Schizophrenia is a severe, chronic psychiatric disorder affecting approximately 24 million people globally, with a lifetime prevalence of about 1% in Iran and a substantial burden in disability-adjusted life years (DALYs) (1). This burden underscores the urgent need for effective, low-cost interventions, such as family-based empowerment programs. Like other chronic conditions, schizophrenia requires continuous long-term care, with nurses serving as frontline providers who maintain prolonged contact with patients and their families (2).
Self-care has emerged as a major concern in chronic disease management (3). Orem defines self-care as a dynamic process involving activities in which individuals engage to maintain their health (4). In schizophrenia, self-care encompasses activities of daily living (Personal hygiene, nutrition, and sleep), medication management, symptom monitoring, coping with stress, and social connection. Deficits in these areas lead to poor outcomes, frequent relapses, and reduced quality of life (5).
Patients with schizophrenia require multiple self-care interventions: medication management for symptom control; psychological and social support to prevent isolation; education about the illness and its management; physical healthcare (Nutrition, exercise, and sleep); and stress-management techniques (6,7). Healthcare providers and families can promote self-care through community-oriented approaches that delegate care responsibilities to patients and their families (8).
Family education is particularly influential in chronic mental illness. Effective training reduces psychological problems, improves health and patient satisfaction, enhances quality of life, ensures continuity of care, reduces complications, shortens hospital stays, increases independence, and enables home-based recovery (9). Research indicates that inadequate education remains a major concern among patients with schizophrenia and their families (10). Empowering families is critical because they provide primary emotional support, help patients understand their emotions and requisites, and must learn about schizophrenia symptoms, treatments, and management strategies to reduce stress (11).
The Family-Centered Empowerment Model enhances family roles in motivation, psychological support, knowledge, attitudes, and perceived threat (12). Empowerment fosters trust, positive adaptation, control, and goal achievement (13). By increasing awareness and self-efficacy, empowerment promotes behavioral self-control, preventive behaviors, health promotion, and improved quality of life (14). Family empowerment creates the capacity for change through nurse-family partnerships and shared responsibility (15). This model has shown positive effects in chronic conditions, including diabetes, heart failure, elderly care, and hemodialysis (16-19). However, no study has specifically examined family-centered care for improving self-care among patients with schizophrenia.
Schizophrenia affects not only the individual but also the family and society, necessitating effective strategies to improve quality of life and reduce the burden of family care (20). The Family-Centered Empowerment Model can improve self-care requisites by increasing family awareness, improving communication, reducing tensions, and enabling patients to cope independently with daily challenges (21). Enhanced self-care reduces symptoms, prevents rehospitalization, improves mental and physical health, and reduces healthcare costs.
Despite the importance of education, many families lack awareness of the specific self-care requisites of patients with schizophrenia and the effective methods for addressing them (22). Sufficient educational resources and family programs focused on self-care skills are lacking (23). Although family-based interventions in schizophrenia have focused on relapse prevention, symptom management, or caregiver psychoeducation, few studies have targeted self-care as the primary outcome, and none have applied the Family-Centered Empowerment Model-which emphasizes perceived threat, problem-solving, and educational participation-to improve daily self-care (22,24,25). This gap justifies the present trial.
Unlike previous studies that focused on relapse prevention or general family psychoeducation, this trial specifically targeted self-care using the structured Family-Centered Empowerment Model among Iranian patients with schizophrenia who had been discharged from a large psychiatric hospital. Therefore, this study aimed to determine the effect of the Family-Centered Empowerment Model on self-care requisites in patients with schizophrenia.
Methods
Design and setting
This randomized controlled trial investigated the effect of the Family-Centered Empowerment Model on self-care requisites in patients with schizophrenia discharged from Razi Hospital in Tabriz, Iran. Razi Hospital is one of the largest teaching hospitals in East Azerbaijan Province and the only center admitting psychiatric patients in the region. It has 18 wards with 650 active beds (591 psychiatric, 68 non-psychiatric) and paraclinical departments. Patients with schizophrenia who were about to be discharged were identified, and their primary caregivers were invited to participate. The primary caregivers then received the training necessary to empower families to improve patients' self-care requisites.
Patients were eligible if they had a diagnosis of schizophrenia according to the Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition (DSM-5), resided in Tabriz, had been discharged from the psychiatric ward of Razi Hospital, provided informed consent (Or consent was obtained from their legal guardian when applicable), adhered to their prescribed medication regimen, and had no comorbid psychiatric disorders (e.g., personality disorders) or severe chronic physical illnesses (e.g., advanced renal or cardiovascular disease) that could interfere with participation. Patients were excluded if they experienced a psychiatric emergency during the study or withdrew their consent.
Primary caregivers were eligible if they were identified by the patient as the family member providing the greatest amount of care, were aged 18 years or older, were able to read and write, had no self-reported mental or psychological illness, and were willing to participate in the study. Caregivers were excluded if they missed more than two consecutive training sessions, were unable to continue participation because of personal circumstances, or declined to continue with the family-centered intervention.
Participants and sampling
The sample size was calculated based on a previous study (26) that reported post-intervention means of 82.08 ± 10.88 (Intervention) and 93.42 ± 16.05 (Control). Although our baseline self-care scores were somewhat worse than those in the reference study, we used a conservative approach: we adopted the larger standard deviation (16.05) from the control group and set the power at 90% to account for potential baseline differences and ensure adequate power to detect a clinically meaningful difference. With a type I error of 0.05 and a mean difference of 10 points, the required sample size was 33 per group; after adding 10% for possible attrition, the final sample was set at 36 per group. This conservative calculation was complemented by the post-hoc sensitivity analysis.
The 72 patients were randomly allocated to the intervention (n = 36) or control (n = 36) group. All 36 participants in each group completed the 8-week intervention and follow-up period; no participants were lost to follow-up, and no one was excluded during the study. Thus, 36 participants in each group (72 in total) were included in the final analysis. A detailed CONSORT flow diagram is provided in Supplementary Figure 1. Although the sample-size calculation anticipated a 10% dropout rate, no attrition occurred during the 8-week study period. All 36 patients in each group completed the post-test assessment.
Data collection
After obtaining official permission from the Research Vice-Chancellor of Qazvin University of Medical Sciences, which supervised the research team, and securing local approval from Tabriz University of Medical Sciences to access Razi Hospital, the research team visited the hospital. Eligible individuals were selected and invited to participate. Written informed consent was obtained from all participants. The patients completed the questionnaires themselves in a quiet room, with the researcher present only to read the items aloud to patients with literacy difficulties or concentration problems. The researcher did not interpret, rephrase, or influence the patients' responses. Eligible patients and their caregivers were selected using purposive sampling from among those discharged from Razi Hospital during the study period. After selection, participants were randomly allocated to the intervention and control groups using block randomization (Block size of 4) to ensure unbiased assignment.
Participants were assigned to the intervention or control group using block randomization (Block size of 4). For 72 participants, 18 blocks were created, each containing 2 intervention and 2 control assignments. Block sequences (e.g., ABAB, AABB, ABBA, and BAAB) were determined using a random-numbers table. To conceal allocation, 72 envelopes were prepared; each random sequence (1 to 18) was recorded on a card and placed in an envelope. The envelopes were sealed and placed sequentially in a box. One envelope was opened at a time, and allocation was based on the block it contained.
Patients who were about to be discharged were identified. The study objectives and procedures were explained to each patient and primary caregiver, and written informed consent was obtained. A pretest was then administered to the patient. Groups of 6-7 participants were formed, and training sessions were conducted as described below. After briefing the patients and their active family members (The primary caregivers identified by the patients), the researcher and an assistant administered the pretests in the psychiatric wards. The following questionnaires were completed: a demographic form (Age, gender, marital status, employment, disease history, etc.) and the Self-Care Requisites Scale in Schizophrenia (SCRS-H) developed by Roldán-Merino (2017) (27). The questionnaire yields a total score ranging from 33 to 165. A lower score indicates a smaller self-care deficit. The questionnaires were completed by the patients themselves.
Both groups received routine psychiatric ward care, including vital-sign monitoring, medication prescription and education, a physician-ordered diet, activity education, and discharge planning. The research team provided no additional intervention to the control group. In the intervention group, the researcher trained the primary caregivers in the ward’s education room after the patients' conditions had stabilized. By agreement with the participants and in consideration of existing constraints, training sessions were held once a week for 8 weeks (9-11 AM). Each session lasted 30-60 minutes. The educational content was designed and implemented based on a needs assessment and the characteristics of the study population. Training was delivered in person using a family-centered approach.
Due to the nature of the educational intervention, it was not possible to blind patients or their primary caregivers to group allocation. However, the outcome assessor who administered the self-care questionnaire was blinded to group assignment to minimize detection bias. The statistician was not blinded to group allocation. All data were collected and entered into the statistical software by a research assistant who was unaware of the study hypotheses.
Intervention
The educational program was based on the Family-Centered Empowerment Model described by Nikrouz et al. (2020) (28). The model consisted of four main steps implemented over 8 weekly sessions for primary caregivers in the intervention group. Sessions were conducted in groups of 6-7 caregivers, who were assigned to groups based on their availability and discharge schedules (Group composition was not randomized). Each session lasted 30 to 60 minutes, depending on the content and group interaction, and was delivered in person in the hospital education room. All sessions were group-based rather than individual to facilitate peer learning and shared problem-solving. A summary of the procedure follows:
Step 1: Perceived threat (Session 1) - Caregivers learned about schizophrenia, its course, symptoms (Positive, negative, cognitive), complications, risk factors, and prognosis. The main goal was to increase awareness and understanding of the disease as a manageable challenge.
Step 2: Problem-solving (Sessions 2-4) - Caregivers were taught necessary self-care requisites for the patient. Content included:
Session 2: Healthy nutrition, physical activity, medication adherence, personal hygiene, interpersonal communication.
Session 3: Identifying and analyzing common patient problems (e.g., non-adherence, communication difficulties) and the family’s role in solving them.
Session 4: Explaining treatment and self-care goals, presenting various solutions for identified problems, and selecting the best solution through group participation.
Step 3: Educational participation (Sessions 5-7) - Sessions were conducted as group discussions and Q&A activities. Caregivers raised practical challenges they encountered when implementing the selected solutions at home. Through discussion and guidance from the researcher, they developed new and more effective solutions. These sessions helped consolidate learning and improve caregivers’ practical skills.
Step 4: Evaluation (Session 8) - The final session assessed caregivers’ knowledge and ability to transfer the information and skills they had learned to patients and other family members. Evaluation was conducted through Q&A activities and group discussion.
It is important to emphasize that patients did not attend the group sessions. Instead, the intervention was designed as a train-the-trainer model: caregivers received knowledge and practical skills during the sessions and were then expected to transfer and practice these skills with the patients at home between sessions. The final evaluation session (Step 4) specifically assessed each caregiver's ability to transfer the learned content to the patient and other family members. Thus, improvement in patients' self-care was achieved indirectly through empowered caregivers, consistent with the core philosophy of the Family-Centered Empowerment Model.
Instruments
Data were collected using a demographic form and the Self-Care Requisites Scale in Schizophrenia (SCRS-H) developed by Roldán-Merino (27). The questionnaires were completed in person by patients as self-reports, with assistance from the researcher when required.
The demographic form included age, gender, education level, occupation, marital status, income level, and disease duration.
The SCRS-H was developed by Roldán-Merino (2017) (27) and culturally adapted for the Iranian population by Kashani Lotfabadi (2022), with a Cronbach’s alpha > 0.70. This scale assesses the self-care requisites of hospitalized patients with schizophrenia (26). It consists of 35 items, each rated on a 5-point scale (1 = no self-efficacy deficit, 5 = complete self-efficacy deficit). Total scores range from 35 to 175; lower scores indicate fewer self-care deficits (i.e., better fulfillment of self-care requisites).
The scale was developed in two stages. First, items based on Orem’s nursing theory were reviewed and approved by a team of 9 mental health specialists and a psychiatrist. Second, psychometric properties were confirmed through confirmatory factor analysis in 264 hospitalized schizophrenia patients (27). Roldán-Merino et al. (2017) confirmed validity and internal consistency (Cronbach’s alpha = 0.94 for the total scale) (27).
Kashani Lotfabadi (2022) adapted the scale for Iran. The translation process was as follows: two Persian-fluent translators translated the scale into Persian; two other translators back-translated the approved Persian version; and a third translator fluent in both languages compared and confirmed the original English and back-translated versions. The Persian translation was then reviewed by a team of 10 clinical psychologists, psychiatrists, and psychiatric nurses. The content-validity indices were CVI = 0.79 and CVR = 0.83 (26). Internal consistency for the total scale was Cronbach’s alpha = 0.88. In the present study, face and content validity were assessed by 10 faculty members of Qazvin University of Medical Sciences, and internal consistency (Cronbach's alpha) was 0.91, indicating excellent reliability. However, construct validity (e.g., confirmatory factor analysis) and test-retest reliability were not re-established for the current sample because the primary aim was to evaluate the intervention effect rather than validate the instrument in this specific population.
Data analysis
Data were analyzed using SPSS version 25. Quantitative variables were described using means and standard deviations, and categorical variables were described using frequencies and percentages. Independent t-tests were used to compare demographic distributions between groups. An independent t-test was also used to compare pre-test self-care scores between the intervention and control groups. To test the hypothesis, analysis of covariance (ANCOVA) was performed with the post-test self-care score as the dependent variable, group as the fixed factor, and pre-test score, patient education level, and caregiver education level as covariates. The educational intervention was provided only to the primary caregivers; patients did not attend the group sessions. Given the borderline interaction between group and pre-test score (P = 0.058) for the homogeneity-of-regression-slopes assumption, a sensitivity analysis was also conducted using a linear mixed-effects model with random intercepts to confirm the robustness of the findings.
Results
A total of 72 patients with schizophrenia and their primary caregivers were randomly assigned to the intervention (n = 36) or control (n = 36) group. The baseline characteristics of patients and caregivers are presented in Tables 1 and 2. The two groups were comparable across most baseline demographic and clinical characteristics. However, significant between-group differences were observed in the education levels of both patients (P = 0.048) and caregivers (P = 0.013). These variables were therefore included as covariates in the adjusted analyses.
The normality of self-care requisites scores in the intervention and control groups was examined separately for the pre-test and post-test and confirmed using histograms and Q-Q plots, as well as the Kolmogorov-Smirnov test (P > 0.05 for all).
As shown in Tables 1 and 2, the intervention and control groups were well matched in terms of baseline demographic and clinical characteristics, supporting the effectiveness of randomisation. Minor imbalances in patient and caregiver education levels were statistically adjusted for as covariates in the primary analysis.
As presented in Table 3, the intervention group showed a significant reduction in self-care requisites scores after the intervention (Post-test: 90.72 ± 12.19), whereas the control group showed little change (Post-test: 100.22 ± 15.03). The between-group difference at the post-test was statistically significant (P = 0.004). Paired t-tests confirmed a significant within-group improvement in the intervention group (Mean change: -4.44 ± 3.12, t = 7.12, P < 0.001), whereas the control group experienced no significant change (Mean change: - 0.20 ± 2.85, t = 0.42, P = 0.678). These within-group findings justified the use of ANCOVA to adjust for baseline differences and covariates.
Levene’s test was used to examine the homogeneity of error variances for the self-care requisites variable. The result (F = 1.22, P = 0.272) showed that the assumption of equal error variances between the groups was met (P > 0.05).
Analysis of covariance assumes a linear relationship between the covariate (Pre-test self-care score) and the dependent variable (Post-test self-care score). The homogeneity-of-regression-slopes assumption concerns the relationship between the covariate and the dependent variable. This assumption was tested by examining whether the interaction between the independent variable (Group) and the covariate (Pre-test score) was statistically significant. The interaction was not significant (F = 2.24, P = 0.058), confirming that the homogeneity-of-regression-slopes assumption was met.
As shown in Table 4, after controlling for pre-test scores, the effect of the intervention on reducing the total self-care requisites score was statistically significant (P < 0.001). The effect size, measured using partial eta squared (η²), was 0.78, indicating that 78% of the variance in post-intervention self-care requisites scores was explained by the Family-Centered Empowerment Model intervention. Because the distributions of patient and caregiver education levels differed significantly between the two groups, we conducted an additional analysis adjusting for these two variables. After controlling for pre-test scores and education levels, the intervention effect on reducing the total self-care requisites score remained statistically significant (P < 0.001). The partial eta squared (η²) effect size was 0.75, indicating that 75% of the variance in the total post-intervention self-care requisites score was explained by the Family-Centered Empowerment Model intervention. The corresponding Cohen's d was 0.69 (95% CI: 0.21 to 1.17).
Because the homogeneity-of-regression-slopes assumption was borderline (Group × pre-test interaction: P = 0.058), we reanalyzed the data using a linear mixed-effects model. The intervention effect remained statistically significant in this sensitivity analysis (β = - 9.21, SE = 0.87, P < 0.001), confirming that the results were robust to the choice of statistical method. Despite the baseline imbalance in education, which could increase error variance, a post-hoc power analysis was performed using the observed effect size (Cohen’s d = 0.69), with α = 0.05 and a sample size of 36 per group. The achieved power was 0.94, indicating that the study had sufficient power (Above the conventional 0.80 threshold) to detect the intervention effect, even after accounting for baseline differences. This result confirms that the observed significant findings were unlikely to be attributable to insufficient power.
|
Table 1. Baseline characteristics of patients in intervention and control groups
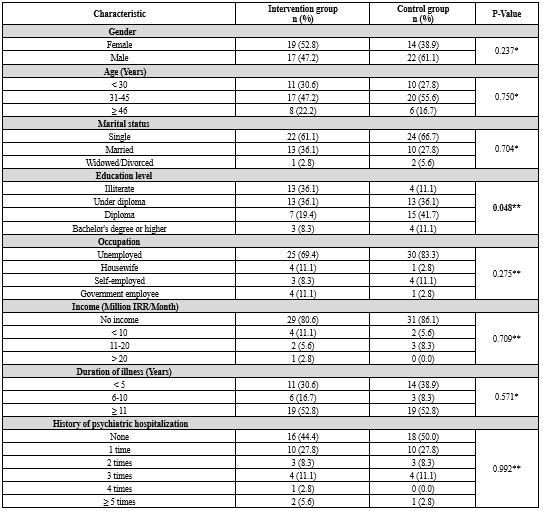 Notes: *Chi-square test, **Fisher's exact test, IRR: Iranian Rial. A statistically significant difference was observed in patients' education level (P = 0.048) between the two groups. |
|
Table 2. Baseline characteristics of caregivers in intervention and control groups
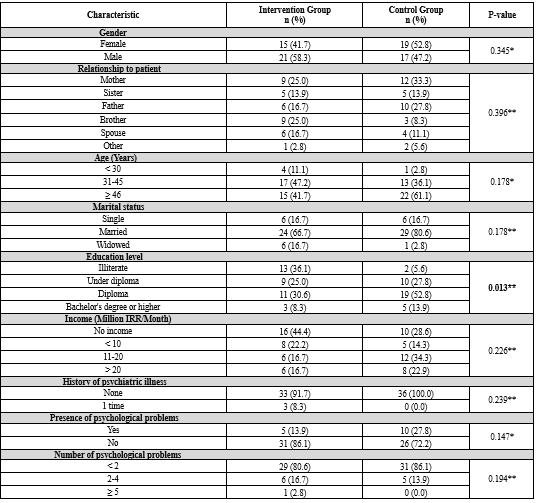 Notes: *Chi-square test, **Fisher's exact test, IRR: Iranian Rial. A statistically significant difference was observed in caregivers' education level (P = 0.013) between the two groups. One data point was missing in the control group for the income variable (n = 35). Table 3. Comparison of self-care requisites scores between and within groups 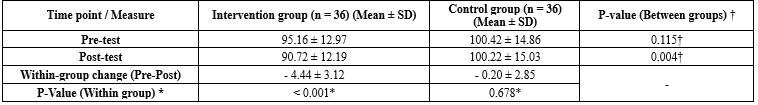 † Independent t test for between group comparisons. *Paired t test was used for within group comparisons. Table 4. ANCOVA results for the effect of intervention on self-care requisites, controlling for pre test scores and education level 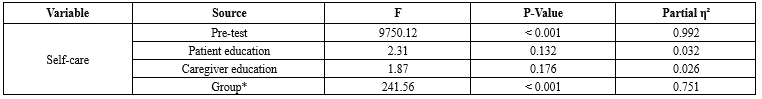 * Cohen’s d for the adjusted mean difference was 0.69 (95% CI: 0.21 to 1.17), confirming a moderate to large effect. |
Discussion
The present randomized controlled trial provides evidence that the Family-Centered Empowerment Model significantly improves the fulfillment of self-care requisites in patients with schizophrenia, as reflected by a significant reduction in SCRS-H scores. The intervention group demonstrated a mean reduction of approximately 4.5 points on the Self-Care Requisites Scale in Schizophrenia (SCRS-H), with a moderate-to-large effect size. This improvement remained significant after controlling for baseline differences and education levels, supporting the robustness of the findings. These findings suggest that training primary caregivers through a structured, family-centered approach can enhance patients' fulfillment of self-care requisites, including those related to activities of daily living, treatment adherence, and health-status monitoring. Improved fulfillment of these self-care requisites may contribute to better community functioning and a reduced risk of relapse.
The observed improvement is consistent with previous family-based interventions in schizophrenia. Rodolico et al. (2022) and Chien et al. (2024), in their systematic reviews, reported that family psychoeducation reduces relapse rates and improves clinical outcomes, though they did not specifically measure self-care (20,9). More directly, Zhou et al. (2020) found that empowerment-based approaches for family caregivers improved patient functioning, while Iswanti et al. (2024) highlighted family empowerment strategies as key to relapse prevention (29,25). Our findings extend this evidence by demonstrating that the Family-Centered Empowerment Model-with its emphasis on perceived threat, problem-solving, and educational participation-can specifically target self-care deficits, an outcome that has received less attention in previous trials.
Several mechanisms may explain this effect. First, the model enhances caregivers' knowledge of schizophrenia and its management, enabling them to provide more informed and consistent support (24). Second, by training caregivers in problem-solving and communication skills, the intervention likely improves the quality of interactions between patients and families, fostering a home environment conducive to self-care practice. Third, Bandura's self-efficacy theory suggests that when family members model and reinforce positive health behaviors, patients develop greater confidence in their own ability to perform self-care tasks (30). This indirect pathway-through the caregiver rather than the patient-may be particularly effective in schizophrenia, where cognitive and motivational deficits often limit the impact of patient-only education.
From a clinical perspective, the Family-Centered Empowerment Model offers several advantages (31). It is relatively low-cost, leverages existing family resources, and can be integrated into routine psychiatric care without requiring extensive additional infrastructure. The group-based format (6-7 caregivers per session) also facilitates peer learning and shared problem-solving, which may enhance caregiver motivation and reduce isolation. These features make the model a practical adjunct to pharmacotherapy, particularly in resource-limited settings where access to specialized mental health services is constrained.
The positive effect of the intervention persisted despite baseline differences in education levels between groups, suggesting that the model may be adaptable across varying socioeconomic backgrounds. Nonetheless, this finding should not be overgeneralized, as the study sample was drawn from a single hospital in Tabriz and may not represent the broader schizophrenia population in Iran. Factors such as symptom severity, medication regimen, illness duration, cognitive functioning, and extra-familial social support-which were not fully controlled-may have influenced outcomes and should be examined in future research.
The legal and ethical considerations associated with family-oriented interventions, including negligence and informed consent, merit attention in future implementation studies (32-34). However, these issues are general to family-based care and do not directly affect the interpretation of our primary findings.
Several limitations should be considered when interpreting these findings. First, the study was conducted in a single psychiatric center with a relatively small sample, which may limit the external validity of the results. Second, blinding of participants and caregivers was not feasible because of the nature of the intervention, although outcome assessment was performed by a blinded assessor to minimize detection bias. Third, residual confounding cannot be excluded, as clinical characteristics such as symptom severity, medication regimen, duration of illness, cognitive functioning, and extra-familial social support were not fully controlled. In addition, self-care was assessed using a self-report instrument, making the findings susceptible to response and social desirability biases, as well as the limited insight commonly observed in schizophrenia. Finally, because the minimal clinically important difference (MCID) for the SCRS-H has not yet been established, the clinical relevance of the observed score changes should be interpreted cautiously. Future studies should evaluate this intervention in larger, multicenter populations with longer follow-up periods, objective outcome measures, and clinically meaningful endpoints to determine the durability and clinical significance of its effects.
Conclusion
This randomized controlled trial demonstrated that the Family-Centered Empowerment Model improved self-care requisites in patients with schizophrenia compared with routine care, as reflected by lower SCRS-H scores. By actively engaging family caregivers in the rehabilitation process, this structured and relatively low-cost intervention has the potential to complement routine psychiatric care and strengthen patients' self-care capacity. Although the findings are encouraging, confirmation in larger multicenter randomized trials with extended follow-up is required before broad implementation can be recommended. Future research should also identify the patient and family characteristics associated with the greatest benefit, clarify the mechanisms underlying the intervention, and establish the minimal clinically important difference for the SCRS-H.
Acknowledgement
The authors would like to thank the patients and their caregivers for their sincere participation. We also appreciate the cooperation of the staff at Razi Hospital, Tabriz, and the Research Vice-Chancellor of Qazvin University of Medical Sciences.
Funding Sources
This research received no specific grant from any funding agency in the public, commercial, or not for profit sectors.
Ethical Statement
The study was approved by the Research Ethics Committee of Qazvin University of Medical Sciences (Approval No. IR.QUMS.REC.1404.001) and was conducted in accordance with the Declaration of Helsinki and relevant national ethical guidelines. Before enrollment, all participants (Patients and their primary caregivers) received clear information about the study objectives, procedures, and their rights. Written informed consent was obtained from all participants prior to data collection. Participation was voluntary, and participants were informed that they could withdraw from the study at any time without affecting their treatment or healthcare services. The confidentiality of all personal and medical information was strictly maintained by anonymizing and securely storing the study data. To ensure equitable access to the educational intervention, caregivers in the control group were provided with a summary training session and educational pamphlets after completion of the study.
Conflicts of Interest
The authors declare no conflict of interest.
Author Contributions
A.T.D: Conceptualization, Investigation, Data collection, Writing - Original draft. M.Sh.: Supervision, Methodology, Project administration, Writing - Review and Editing. M.V: Investigation, Validation, Writing - Review and Editing. M.R: Formal analysis, Software, Data curation. All authors read and approved the final manuscript.
Data Availability Statement
The data supporting the findings of this study are available from the corresponding author upon reasonable request, subject to ethical restrictions.
Use of Artificial Intelligence
We used AI to improve the language. After using this service, the authors reviewed and edited the content as needed and take full responsibility for the content of the published article.
Type of study: Original Article |
Subject:
Psychology and Psychiatry
References
1. Charlson FJ, Ferrari AJ, Santomauro DF, Diminic S, Stockings E, Scott JG, et al. Global epidemiology and burden of schizophrenia: findings from the Global Burden of Disease Study 2016. Schizophr Bull. 2018;4(6):1195-203. [View at Publisher] [DOI] [PMID] [Google Scholar]
2. Hanoun J, Beloni P, Toniolo J. Role of nurses in the management of noncommunicable diseases in Middle Eastern countries: A scoping review. Nurs Outlook. 2025;73(4):102479. [View at Publisher] [DOI] [PMID] [Google Scholar]
3. Pimpão PA, Goes M, Marques MC, Cardoso IC, Oliveira H. Effectiveness of Nursing Interventions in Promoting Self-Care Among Adults: A Systematic Review Protocol and Meta-Analysis. In: Gerontechnology VI: Contributions to the Seventh International Workshop on Gerontechnology (IWoG 2024). Cham: Springer Nature Switzerland; 2025. p. 225-34. [View at Publisher] [DOI] [Google Scholar]
4. Riegel B, Jaarsma T, Strömberg A. An update to the middle-range theory of self-care of chronic illness. ANS Adv Nurs Sci. 2026;49(1):14-25. [View at Publisher] [DOI] [PMID] [Google Scholar]
5. Johansen KK, Møller J, Hansen JP, Hounsgaard L, Fluttert F. Early recognition method for patients with schizophrenia or bipolar disorder in community mental health care. J Clin Nurs. 2022;31(23-24):3535-49. [View at Publisher] [DOI] [PMID] [Google Scholar]
6. Ehrlich C, Chester P, Kisely S, Crompton D, Kendall E. Making sense of self-care practices at the intersection of severe mental illness and physical health -An Australian study. Health Soc Care Community. 2018;26(1):e47-55. [View at Publisher] [DOI] [PMID] [Google Scholar]
7. Vaghee S, Modarres Gharavi M, Asgharipour N, Chamanzari H. The effect of stress management training on positive experiences of families caring for patients with schizophrenia. Evid Based Care. 2017;6(4):57-65. [View at Publisher] [DOI] [Google Scholar]
8. Wilkinson A, Whitehead L. Evolution of the concept of self-care and implications for nurses: a literature review. Int J Nurs Stud. 2009;46(8):1143-7. [View at Publisher] [DOI] [PMID] [Google Scholar]
9. Chien WT, Ma DCF, Bressington D, Mou H. Family-based interventions versus standard care for people with schizophrenia. Cochrane Database Syst Rev. 2024;10(10):CD013541. [View at Publisher] [DOI] [PMID] [Google Scholar]
10. Bland R, Darlington Y. The nature and sources of hope: perspectives of family caregivers of people with serious mental illness. Perspect Psychiatr Care. 2002;38(2):61-8. [View at Publisher] [DOI] [PMID] [Google Scholar]
11. Shokraneh E, Ahmadi S. The effects of family cognitive training on improving the treatment of schizophrenic patients. J Fam Res. 2009;5(1):17-28. [View at Publisher] [Google Scholar]
12. Alhani F. Design and evaluation of family-centered empowerment model to prevent iron deficiency anemia [dissertation]. Tehran: Tarbiat Modarres University; 2003. [View at Publisher]
13. Won CW, Fitts SS, Favaro S, Olsen P, Phelan EA. Community-based "powerful tools" intervention enhances health of caregivers. Arch Gerontol Geriatr. 2008;46(1):89-100. [View at Publisher] [DOI] [PMID] [Google Scholar]
14. Timby BK, Smith NE. Essentials of Nursing: Care of Adults and Children. Lippincott Williams & Wilkins; 2005. [View at Publisher] [Google Scholar]
15. Auld ME, Henley M. Environmental health promotion: advancing the science and practice . Health Promot Pract. 2010;11(3):301-2. [View at Publisher] [DOI] [PMID] [Google Scholar]
16. Razmaraei S, Hemmati MM, Khalkhali HR. The effect of family-centered education on self-care in patients with type 2 diabetes. J Urmia Nurs Midwifery Fac. 2016;14(2):118-27. [View at Publisher] [Google Scholar]
17. Ghajar A, Esmaeili R, Yazdani-Charati J, Ashrafi Z, Mazdaran S, Heidari Gorji MA. Effect of family-centered education on hope in patients with heart failure. J Mazandaran Univ Med Sci. 2018;28(166):71-80. [View at Publisher] [Google Scholar]
18. Tabari F, Zakerimoghadam M, Hejazi ZS. The effect of the family-centered educational program on medication management in elderly patients with ischemic heart disease. Iran J Nurs Res. 2019;14(1):14-20. [View at Publisher] [Google Scholar]
19. Salar A, Kermansaravi F, Navidian A, Taheri B. The effect of a family-centered empowerment model on quality of life in dialysis patients. Payesh. 2018;17(2):179-90. [View at Publisher] [Google Scholar]
20. Rodolico A, Bighelli I, Avanzato C, Concerto C, Cutrufelli P, Mineo L, et al. Family interventions for relapse prevention in schizophrenia: a systematic review and network meta-analysis. Lancet Psychiatry. 2022;9(3):211-21. [View at Publisher] [DOI] [PMID] [Google Scholar]
21. Mohammad Mousaei F, Zendehtalb HR, Zare M, Behnam Vashani HR. Effect of Family-centered Empowerment Model on Self-care Behaviors of Patients with Multiple sclerosis. EBC. 2021;11(3):35-43. [View at Publisher] [DOI] [Google Scholar]
22. Thorne S, Hislop TG, Kim-Sing C, Oglov V, Oliffe JL, Stajduhar KI. Changing communication needs and preferences across the cancer care trajectory: insights from the patient perspective. Support Care Cancer. 2014;22(4):1009-15. [View at Publisher] [DOI] [PMID] [Google Scholar]
23. Gleeson JFM, Ludwig K, Stiles BJ, Piantella S, McNab C, Cotton S, et al. Systematic review and meta-analysis of family-based interventions for early psychosis: carer and patient outcomes. Schizophr Res. 2025;276:57-78. [View at Publisher] [DOI] [PMID] [Google Scholar]
24. Hodé Y, Winter H, Willard D, et al. Does psychoeducation for families have an effect when only one caregiver is present and the patient is not involved? World Soc Psychiatry. 2024;6(1):30-6. [View at Publisher] [DOI] [Google Scholar]
25. Iswanti DI, Nursalam N, Fitryasari R, Mendrofa FAM, Kandar K. Family empowerment strategies for relapse prevention in individuals with schizophrenia: a scoping review. J Psychosoc Nurs Ment Health Serv. 2024;62(5):19-27. [View at Publisher] [DOI] [PMID] [Google Scholar]
26. Kashani Lotfabadi M, Bayazi MH, Rajaei AR. The effect of cognitive-behavioral group training of self-care skills on self-care in patients with schizophrenia. Nursing Practice Today. 2022; 9(1):24-36. [View at Publisher] [DOI] [Google Scholar]
27. Roldán‐Merino J, Miguel-Ruiz D, Lluch‐Canut MT, Puig‐Llobet M, Feria‐Raposo I, Group QW. Psychometric Properties of S elf‐C are R equisites S cale (SCRS‐h) inHospitalized Patients Diagnosed With Schizophrenia. Perspect Psychiatr Care. 2017;53(1):1628. [View at Publisher] [DOI] [PMID] [Google Scholar]
28. Nikrouz L,Alhani F, Ebadi A, Kazemnejad A. The concept of self-control in the family caregivers of patients with chronic disease based on the family-centered empowerment model: A qualitative directed content analysis. . Hayat. 2020;26(2):218-37. [View at Publisher] [Google Scholar]
29. Zhou D-HR, Chiu Y-LM, Lo T-LW, Lo W-FA, Wong S-S, Luk K-L, et al. Outside-in or inside-out? A randomized controlledtrial of two empowerment approaches for family caregivers of people with schizophrenia. Issues Ment Health Nurs. 2020;41(9):761-72. [View at Publisher] [DOI] [PMID] [Google Scholar]
30. Bandura A. Self-efficacy: The exercise of control. New York: WH. Freeman and Company. 1997. [View at Publisher]
31. Lin X, Fei F, Zhang X, Zhou Y, Qin F, Sun X, et al. Effectiveness of the Family-Centred Empowerment Model on Informal Caregivers of People With Chronic Diseases: A Systematic Review and Meta-Analysis. J Clin Nurs. 2026;35(2):602-20. [View at Publisher] [DOI] [PMID] [Google Scholar]
32. Abdi M, Norouzi A, Mafinejad MK. Development and Psychometric Validation of a Questionnaire to Assess Attitudes Toward Medical Law Reasoning (MLRAQ). Int J Clin Pract. 2025:5167920. [View at Publisher] [DOI] [Google Scholar]
33. Torkmandi H, Sadeghi B, Farmahin Farahany P, Mozafari M, Abdi M. Legal and Ethical Recommendations for Video Recording in the Operating Room: A Review of Literature. JIMC. 2024;7(2):238-45. [View at Publisher] [DOI] [Google Scholar]
34. Shiri R, Torkmand H, Abdi M. Informed Consent in Elective Orthopedic Surgeries: A Scoping Review of Medico‐Legal Challenge and Team‐Based Application. ANZ J Surg. 2026;96(6):1424-41. [View at Publisher] [DOI] [PMID] [Google Scholar]
Send email to the article author
| Rights and permissions | |
 |
This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License. |
